What Makes the Accessory Nerve Special?
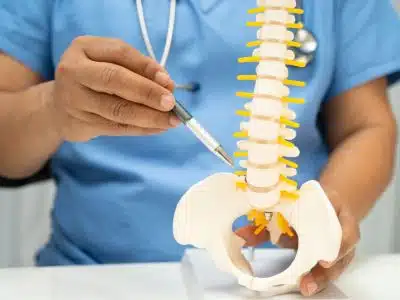
The accessory nerve is truly unique among the cranial nerves. Unlike its cousins that originate entirely in the brain, this nerve has a fascinating journey. It actually starts in your upper spinal cord (specifically from nerve roots C2-C6), travels up through the base of your skull, then loops back down to control two major muscles:
- The trapezius muscle – that large triangular muscle spanning your upper back and shoulders
- The sternocleidomastoid muscle – the prominent neck muscle you can see when you turn your head
This unusual pathway makes the accessory nerve particularly vulnerable to injury at multiple points along its journey. When this nerve or its muscles don’t work well, you might feel pain, stiffness, or muscle tightness in your neck and shoulders NCBI.
How Do You Know If Your Accessory Nerve Is Affected?
Recent research published in 2024 shows that accessory nerve dysfunction often presents with a specific cluster of symptoms. All patients presented with a cluster of signs and symptoms, including trapezius atrophy, shoulder girdle depression, limited active shoulder abduction to less than 90°, shoulder pain, and shoulder weakness Journal of Orthopaedic & Sports Physical Therapy.
Common signs include:
- Difficulty lifting your arm above shoulder height
- A drooping shoulder on one side
- Pain that travels from your neck into your shoulder blade
- Weakness when trying to shrug your shoulders
- Difficulty turning your head against resistance
What’s particularly interesting is that approximately 90% of patients regained the ability to at least elevate their arm to 90 degrees of abduction MedLink when appropriate treatment was provided, highlighting the importance of proper diagnosis and intervention.
The Science Behind Multimodal Treatment
Here’s where things get interesting for those dealing with neck and shoulder pain. Recent research from 2020-2024 consistently shows that a multimodal approach – combining different treatment methods – provides superior results compared to single treatments alone.
A 2020 study examining combination therapies found that Combination therapies (MET plus ICT) showed immediate and short-term (2-week follow-up) improvements in neck pain and muscle tenderness in male patients with upper trapezius active MTrPs NCBI. This reinforces what we see clinically – that addressing nerve-related pain from multiple angles yields better outcomes.
How Chiropractic Care Fits Into Your Recovery
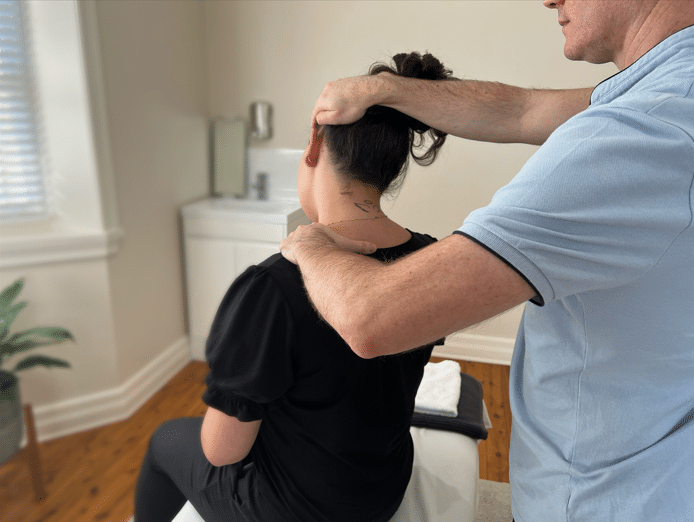
When it comes to nerve-related neck and shoulder pain, chiropractic care can play a valuable role in a comprehensive treatment plan. But let’s be clear about what the research actually shows.
Spinal adjustments may help by:
- Improving joint mobility in the cervical and thoracic spine
- relieving pressure on nerves and facilitating the body’s innate healing processes Heartlandchiropracticcenter
- Reducing muscle tension in surrounding areas
- Optimizing nerve signal transmission
A 2024 case report documented a patient with accessory nerve injury following spinal manipulation who responded to nonsurgical measures over 18 months PubMed Central, demonstrating that while complications can occur, conservative management often leads to recovery.
The Critical Role of Exercise and Rehabilitation
Perhaps the most important finding from recent research is the essential role of targeted exercise in recovery. The deep cervical flexors include the longus coli, longus capitus, rectus capitis anterior, and rectus capitis lateralis, which function in a dynamic fashion to support the neck when it is in neutral or mid-range postures that commonly occur during functional daily activities PubMed Central.
Key exercises that research supports include:
Deep neck flexor strengthening: These small but mighty muscles provide crucial support for your cervical spine
Lower trapezius exercises: A lower trapezius strengthening exercise program is an effective method with clinical significance for reducing the level of neck dysfunction, and improving the postural alignment, muscle thickness, and contraction rate of the lower trapezius muscle NCBI
Scapular stabilization work: Targeting muscles like the rhomboids and serratus anterior to improve shoulder blade control
What This Means for Your Cervical Pain
If you’re dealing with neck pain that extends into your shoulders, understanding the role of the accessory nerve can be a game-changer. Physical and occupational therapy are useful ways of providing significant functional benefits NCBI, with studies showing that early intervention leads to better outcomes.
The key takeaway? A comprehensive approach works best. Research from 2024 demonstrated that a multimodal treatment programme, whihch was performed on all pilots within 48 hours after the last flight Wiley Online Library, showing significant improvements in pain and function when treatment was initiated promptly.
Practical Steps You Can Take Today
Based on the latest evidence, here’s what you can do:
- Don’t wait: Early assessment and treatment show better outcomes than delayed intervention
- Embrace a team approach: Combining manual therapy, specific exercises, and proper ergonomics creates the best results
- Stay consistent: Research shows that improvements require regular treatment and exercise over several weeks
- Address posture: Forward head posture and rounded shoulders increase stress on the accessory nerve pathway