Sciatica treatment in 2026. When to do sciatica surgery?

Learn more about how your body works

Introduction

That shooting pain down your leg is hard to ignore. It might start as a dull ache in your lower back, then turn into a burning line that runs through your buttock, down the back of your thigh, and sometimes all the way to your foot. You have probably already asked yourself the big question. Does this settle on its own, or am I looking at surgery? The honest answer in 2026 is that most people never need an operation, but a clear subset genuinely do, and knowing which group you are in changes everything about how you approach the next few weeks.

Pififormis syndrome causing sciatic nerve pain. Anatomical image of person with muscle pushing on nerve drawn.

Key takeaways

  • Most sciatica settles with conservative care alone. Guidelines recommend a genuine 6 to 8 week trial of non-operative treatment before considering surgery, since randomised trial evidence shows early surgery only speeds up recovery rather than improving how patients feel at one, two, or five years.

  • If severe sciatica from a confirmed disc herniation has not meaningfully improved after 6 to 12 weeks (or persists for 4 to 12 months), discectomy has moderate-quality trial evidence showing clearer and faster pain relief than continuing conservative care alone.

  • Bladder or bowel changes, saddle numbness, or rapidly worsening leg weakness alongside sciatica are signs of cauda equina syndrome, a surgical emergency where current evidence supports decompression within 24 to 48 hours regardless of how long the back pain itself has been present.

Am I actually experiencing sciatica?

Sciatica describes pain that travels along the path of your sciatic nerve, the widest and longest nerve in your body. It forms from spinal nerves in your lower back and sacrum joining together, then running under your piriformis muscle and down the back of your leg.

The pain itself has a fairly recognisable signature. It is often sharp, shooting, and burning rather than a plain ache. It usually starts as back pain, then develops numbness, tingling, or a pins-and-needles sensation as it travels. Some people also notice their foot or leg feels clumsy, which is muscle weakness showing up as a change in how they walk. Movement, prolonged sitting, or even coughing can make it worse.

Think of your sciatic nerve like a garden hose running from a tap at your spine down to a sprinkler at your foot. Kink the hose anywhere along its length, at the tap end or somewhere in the middle, and the water pressure drops all the way down the line. Sciatica works the same way. Compression can happen high up near your spinal nerve roots or lower down where the nerve passes through muscle.

What is actually compressing the nerve?

Sciatica is not a diagnosis on its own. It is a description of a symptom pattern, and your treatment depends entirely on what is doing the compressing.

The most common cause is a lumbar disc herniation narrowing the space around your nerve root, often alongside degenerative changes such as bone spurs or age-related disc wear. This is sometimes described as lumbar spinal stenosis. Far less commonly, compression can come from a growing lesion, an infection, or a fracture in the lumbar spine.

Compression can also happen further down the line, where the sciatic nerve passes beneath your piriformis muscle in the buttock. When a tight or irritated piriformis muscle squeezes the nerve, it is called piriformis syndrome, and it can feel remarkably similar to a disc-related problem even though the treatment approach differs.

When leg pain is a medical emergency

Most sciatica is uncomfortable rather than dangerous. A small number of presentations are genuinely urgent, and it is worth knowing the difference.

If you notice new bladder or bowel changes, numbness in your inner thighs or groin (often described as saddle numbness), or sexual dysfunction on top of your back and leg pain, this can signal cauda equina syndrome (Lavy and colleagues, International Orthopaedics, 2021). This is compression of the nerve bundle at the very base of your spinal cord, and it is a different problem to ordinary sciatica. Left untreated, it can cause permanent nerve damage. If you notice any of these signs, do not wait for a routine appointment. Go straight to your nearest emergency department.

How sciatica is diagnosed in 2026

Diagnosis still starts the old-fashioned way, with a thorough history and a hands-on physical and neurological examination. Your practitioner is checking your reflexes, your strength, and your sensation, and testing how your nerve responds to specific movements.

Imaging, usually an MRI, is not always needed straight away. It becomes useful when your symptoms persist, when there are neurological changes, or when surgery is genuinely being considered, because it shows whether a herniated disc or another structural issue is compressing your nerve root or spinal canal.

What treatment actually looks like first

Here is the reassuring part. International guidelines are consistent on this point. Non-operative care remains the first-line treatment for sciatica unless there is a significant neurological deficit or cauda equina syndrome (Neurospine, 2025; Frontiers in Surgery, 2025).

That usually means a combination of hands-on treatment, guided exercise, and time. Physical therapy and manual therapy aim to improve your mobility, calm your symptoms, and rebuild the strength of your core and back muscles so they can share the load your spine has been carrying alone. Over-the-counter anti-inflammatory medication or, occasionally, a short course of muscle relaxants can help take the edge off while that work happens.

Most guidelines suggest giving conservative care a genuine trial of around six to eight weeks before considering anything more invasive (Neurospine, 2025). That is not us being slow. It reflects how disc material genuinely behaves over time, often shrinking and settling with the body’s own healing process.

Do epidural steroid injections actually help?

They can, a little. A 2020 Cochrane review of 25 placebo-controlled trials found epidural corticosteroid injections were probably slightly more effective than a placebo injection at reducing leg pain and disability in the short term, though the effect was small and did not last much beyond a few months (Oliveira and colleagues, Cochrane Database of Systematic Reviews, 2020). A more recent 2025 review of 72 trials found similar results, with injections outperforming other conservative options but not matching the long-term relief that surgery provides when surgery is genuinely indicated (PMC, 2025).

So think of a steroid injection like putting out a spot fire. It can calm inflammation enough to buy you a window to keep doing your rehab, but it is not putting out the underlying blaze if a disc is still pressing on the nerve.

When should sciatica surgery actually be considered in 2026?

This is the question you came here for, so let us be direct about what the current evidence actually shows.

There are two very different situations. The first is a genuine emergency. If you have cauda equina syndrome, progressive or severe muscle weakness, or rapidly worsening neurological function, surgery is not really optional and should happen urgently. A 2025 systematic review and meta-analysis pooling more than 26,000 cases found that decompression within 48 hours of symptom onset significantly improved bladder recovery, motor function, and overall neurological outcomes compared with waiting longer than 48 hours, particularly for people whose bladder function was only partially affected (Reassessing the Clock in Cauda Equina Syndrome, 2025). Interestingly, a large UK cohort study did not find the same clear link between timing and one-year outcomes, and instead found that how severe your symptoms were at presentation mattered more than the exact hour of surgery (Woodfield and colleagues, Lancet Regional Health Europe, 2022). We are honest that the research community is still refining this picture, but the practical guidance has not changed. Bladder or bowel dysfunction alongside sciatica symptoms warrants surgical review within 24 to 48 hours.

The second situation is ordinary, non-emergency sciatica from a disc herniation that simply is not settling. Here, the evidence is more nuanced than you might expect, and it is worth knowing before you make a decision.

A well-known Dutch trial randomised 283 patients with 6 to 12 weeks of sciatica to either early microdiscectomy or continued conservative care with the option of later surgery. Early surgery relieved leg pain roughly twice as fast, but by one year, 95 percent of both groups had recovered well, and that similarity held at two years and five years (Peul and colleagues, New England Journal of Medicine, 2007; BMJ, 2008). Around 44 percent of the conservative group ended up choosing surgery anyway because their pain had not eased enough.

For sciatica that has been running much longer, the picture shifts. A single-centre US trial randomised 128 patients with sciatica lasting 4 to 12 months to either microdiscectomy or 6 months of structured non-operative care. This time, surgery clearly won on leg pain at 6 months (Bailey and colleagues, New England Journal of Medicine, 2020). A 2023 systematic review and meta-analysis of 24 trials backed this up, finding that discectomy gave a moderate reduction in leg pain compared with non-surgical treatment in the short and medium term, though the benefit shrank over time and the certainty of the evidence was rated low (Fernandez and colleagues, BMJ, 2023).

So how do the guidelines translate this into a practical rule of thumb? Most current recommendations suggest surgery becomes a reasonable option when severe sciatica has not meaningfully improved after 6 to 12 weeks of genuine conservative care, when there is a clearly matching structural finding on imaging such as a herniated disc, and when your symptoms are significantly limiting your daily life (ISASS Policy Guideline, 2021; Frontiers in Surgery, 2025). It is not a race, and it is not a failure if you get there. It is simply what the evidence supports once conservative care has had a fair chance to work.

What surgery does and does not fix

A discectomy removes the portion of disc material pressing on your nerve root. It is genuinely effective at relieving the mechanical compression causing your leg pain, and most people feel real relief.

What it does not automatically fix is the years of deconditioning, guarded movement patterns, and reduced core control that often built up while you were in pain. That is why a structured rehabilitation plan after surgery matters just as much as the operation itself. Removing the kink in the hose does not retrain the muscles that were compensating for it the whole time.

Preventing sciatica in the first place

Posture matters more than people expect. Habitually poor sitting posture reduces space and movement in your lower spine over time, which can contribute to both back pain and sciatica developing in the first place.

If you already live with chronic sciatica, self-care between sessions genuinely helps maintain the gains you make in the clinic. Heat therapy, gentle stretching, and a consistent movement routine keep inflammation and pain levels lower day to day. Self-care alone is rarely enough for an acute flare, though, which is exactly why proper assessment matters early, before short-term pain has the chance to become a long-term pattern.

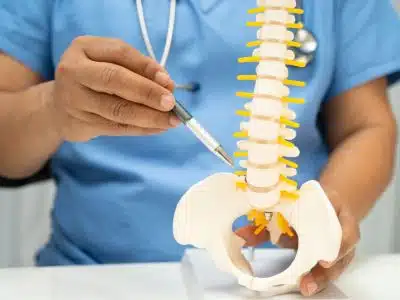
Anatomy of spine in plastci model. Depiciting lower back. Pain at lower disc shown in red. Can be caused by osteoarthritis

Summary

Sciatica is common, and it can affect people at almost any age. It shows up as pain radiating from your lower back down your leg, often with numbness, tingling, or a burning quality, and in more advanced cases, muscle weakness or foot drop.

Degenerative disc and joint changes are one of the leading causes we see in the clinic, and they are frequently linked to years of underused spinal muscles rather than a single injury. Building and maintaining strength and control around your spine, starting well before you have a problem, genuinely reduces your risk.

If you are experiencing sciatica right now, treatment typically starts with conservative care to settle your pain, restore your postural control, and retrain how you move day to day. For most people, this is enough. For a smaller group, particularly those with severe pain lasting beyond 6 to 12 weeks, progressive neurological changes, or cauda equina symptoms, surgery becomes the appropriate next step, and it can offer real and lasting relief. Whichever path you are on, an active rehabilitation plan afterwards is what protects your results long term.

If you are dealing with sciatica in Five Dock or the Inner West and want a proper assessment of where you sit on this spectrum, get in touch. We are always happy to help.

This article is general information only and is not a substitute for an individual assessment by a qualified health practitioner. If you notice bladder or bowel changes, saddle numbness, or rapidly worsening leg weakness, seek emergency care immediately.

Bibliography

  1. Lavy, C., Marks, P., Dangas, K., & Todd, N. (2021). Cauda equina syndrome — A practical guide to definition and classification. International Orthopaedics, 46(2), 165–169. https://pmc.ncbi.nlm.nih.gov/articles/PMC8782783/

  2. A Systematic Review of Treatment Guidelines for Lumbar Disc Herniation with Radiculopathy. Neurospine, 2025. https://www.e-neurospine.org/journal/view.php?number=1714

  3. Recent advances and evolving strategies in the treatment of lumbar disc herniation. Frontiers in Surgery (PMC), 2025. https://pmc.ncbi.nlm.nih.gov/articles/PMC12757302/

  4. Oliveira, C. B., Maher, C. G., Ferreira, M. L., et al. (2020). Epidural corticosteroid injections for lumbosacral radicular pain. Cochrane Database of Systematic Reviews, CD013577. https://www.cochrane.org/evidence/CD013577_corticosteroid-injections-treatment-sciatica

  5. Epidural steroid injections in lumbar disc herniation: a systematic review. PMC, 2025. https://pmc.ncbi.nlm.nih.gov/articles/PMC11979942/

  6. Reassessing the clock in cauda equina syndrome: a systematic review and meta-analysis of surgical timing and outcomes, 2025. https://pubmed.ncbi.nlm.nih.gov/41991105/

  7. Woodfield, J., et al. (2022). Presentation, management, and outcomes of cauda equina syndrome up to one year after surgery. Lancet Regional Health Europe. https://www.thelancet.com/journals/lanepe/article/PIIS2666-7762(22)00241-1/fulltext

  8. Peul, W. C., et al. (2007). Surgery versus prolonged conservative treatment for sciatica. New England Journal of Medicine, 356(22), 2245–2256. https://www.nejm.org/doi/full/10.1056/NEJMoa064039

  9. Peul, W. C., et al. (2008). Prolonged conservative care versus early surgery in patients with sciatica: two year results of a randomised controlled trial. BMJ, 336(7657), 1355–1358. https://www.bmj.com/content/336/7657/1355

  10. Bailey, C. S., et al. (2020). Surgery versus conservative care for persistent sciatica lasting 4 to 12 months. New England Journal of Medicine, 382(12), 1093–1102. https://pubmed.ncbi.nlm.nih.gov/32187469/

  11. Fernandez, M., et al. (2023). Surgical versus non-surgical treatment for sciatica: systematic review and meta-analysis of randomised controlled trials. BMJ, 381, e070730. https://www.bmj.com/content/381/bmj-2022-070730

  12. ISASS Policy Guideline: Surgical Treatment of Lumbar Disc Herniation with Radiculopathy, 2021. https://isass.org/isass-policy-guideline-surgical-treatment-of-lumbar-disc-herniation-with-radiculopathy/

Subscribe for our free health tips

About the Author

Doctor Scott McEvoy head shot. Doctor McEvoy is wearing a black shirt and smiling.

Dr Scott McEvoy

Scott has more than 20 years of clinical experience as a movement expert and musculoskeletal health professional.  His thorough understanding of how pain affects your spine, joints, muscles, and total well-being is the result of significant academic study and many many years of clinical experience.   Scott’s real interest in movement mechanics enables him to develop individualised care plans that summarise complex problems into clear, simple treatments, leading to quicker healing times. His friendly, attentive approach ensures that you not only comprehend but also feel supported throughout your treatment journey, allowing you to return to the things you like with restored confidence and vitality.

Chiropractic
Learn about how chiropractic can help you
Osteopath
Learn about how osteopath can help you
Functional Exercise
Exercise can be fun and easy. One exercise can change alot
Massage
There are both relaxing and therapeutic benefits to massage
Health Span
How looking after yourself along the way pays off
Five Dock Osteo Chiro
A bit about how we can help you

Do You Want To Feel Better?

drop us a line and keep in touch

Five Dock Osteopathic and Chiropractic male chiropractor wearing a light blue shirt performing a stretch on the neck of a young female patient. The doctors right hand is placed on the head of the patient and the left hand on the shoulder of the female patient

Bibliography

  1. García-González, J., Romero-del Rey, R., Martínez-Martín, V., Requena-Mullor, M., & Alarcón-Rodríguez, R. (2024). Comparison of Short-Term Effects of Different Spinal Manipulations in Patients with Chronic Non-Specific Neck Pain: A Randomized Controlled Trial. Healthcare, 12(13), 1348.
  2. Rubinstein, S. M., de Zoete, A., van Middelkoop, M., Assendelft, W. J., de Boer, M. R., & van Tulder, M. W. (2019). Benefits and harms of spinal manipulative therapy for the treatment of chronic low back pain: systematic review and meta-analysis of randomised controlled trials. BMJ, 364, l689.
  3. Gevers-Montoro, C., Provencher, B., Descarreaux, M., Ortega de Mues, A., & Piché, M. (2021). Clinical Effectiveness and Efficacy of Chiropractic Spinal Manipulation for Spine Pain. Frontiers in Pain Research, 2, 765921.
  4. Tsegay, G. S., Gebregergs, G. B., Weleslassie, G. G., & Hailemariam, T. T. (2023). Effectiveness of Thoracic Spine Manipulation on the Management of Neck Pain: A Systematic Review and Meta-Analysis of Randomized Control Trials. Journal of Pain Research, 16, 597-609.
  5. Waqas, M. S., Karimi, H., Ahmad, A., Rafiq, S., Anwar, N., & Liaqat, S. (2023). The Effects of Spinal Manipulation Added to Exercise on Pain and Quality of Life in Patients with Thoracic Spinal Pain: A Randomized Controlled Trial. BioMed Research International, 2023, 7537335.
  6. Chu, E. C., Trager, R. J., Lee, L. Y., & Niazi, I. K. (2023). A retrospective analysis of the incidence of severe adverse events among recipients of chiropractic spinal manipulative therapy. Scientific Reports, 13(1), 1254.
  7. Trager, R. J., & Young, J. J. (2024). Chiropractic and Spinal Manipulation: A Review of Research Trends, Evidence Gaps, and Guideline Recommendations. Archives of Physical Medicine and Rehabilitation, 105(10), 1870-1881.
  8. Bronfort, G., Evans, R., Anderson, A. V., Svendsen, K. H., Bracha, Y., & Grimm, R. H. (2012). Spinal manipulation, medication, or home exercise with advice for acute and subacute neck pain: a randomized trial. Annals of Internal Medicine, 156(1), 1-10.
  9. Corcoran, K. L., Bastian, L. A., Gunderson, C. G., Steffens, C., Brackett, A., & Lisi, A. J. (2020). Association between chiropractic use and opioid receipt among patients with spinal pain: a systematic review and meta-analysis. Pain Medicine, 21(2), e139-e145.
  10. Liliedahl, R. L., Finch, M. D., Axene, D. V., & Goertz, C. M. (2010). Cost of care for common back pain conditions initiated with chiropractic doctor vs medical doctor/doctor of osteopathy as first physician: experience of one Tennessee-based general health insurer. Journal of Manipulative and Physiological Therapeutics, 33(9), 640-643.

Subscribe for our free health tips

About the Author

Doctor Scott McEvoy head shot. Doctor McEvoy is wearing a black shirt and smiling.

Dr Scott McEvoy

Scott has more than 20 years of clinical experience as a movement expert and musculoskeletal health professional.  His thorough understanding of how pain affects your spine, joints, muscles, and total well-being is the result of significant academic study and many many years of clinical experience.   Scott’s real interest in movement mechanics enables him to develop individualised care plans that summarise complex problems into clear, simple treatments, leading to quicker healing times. His friendly, attentive approach ensures that you not only comprehend but also feel supported throughout your treatment journey, allowing you to return to the things you like with restored confidence and vitality.

Chiropractic
Learn about how chiropractic can help you
Osteopath
Learn about how osteopath can help you
Functional Exercise
Exercise can be fun and easy. One exercise can change alot
Massage
There are both relaxing and therapeutic benefits to massage
Health Span
How looking after yourself along the way pays off
Five Dock Osteo Chiro
A bit about how we can help you

Do You Want To Feel Better?

drop us a line and keep in touch

Five Dock Osteopathic and Chiropractic male chiropractor wearing a light blue shirt performing a stretch on the neck of a young female patient. The doctors right hand is placed on the head of the patient and the left hand on the shoulder of the female patient

Am I experiencing sciatica pain?

Sciatica is a term often used to describe sciatic nerve pain. It refers to pain that radiates along the path of the sciatic nerve. Pain is often felt in the lower back, buttocks, back of the leg, and may reach the foot or toes.

Sciatica pain is described as.

Pain is described as a sharp, shooting pain that is burning in nature. Usually starting off as back pain, it is later accompanied by development of numbness, tingling, pins-and-needles sensation in the affected leg. Some people also experience muscle weakness in the leg or foot which results in clumsiness when walking. Symptoms of sciatica may worsen with movement, prolonged sitting, or coughing.

Sciatica Pain starts in the back and refers down your leg to the foot or ankle.

What causes sciatica pain?

Sciatica is pain resulting from compression of the sciatic nerve. Symptoms associated with sciatica are therefore similar to symptoms caused by pinched nerves. Compression can occur along the length of the sciatic nerve or at the level of the spinal cord, nerve roots, or spinal nerves before they form the sciatic nerve.

Sciatica pain due to spinal stenosis.

Compression may be a result of lumbar spinal stenosis or the narrowing of the spinal canal in the lumbar spine as a result of herniated discs associated with degenerative disc disease and arthritis-related changes such as development of bone spurs. In rare cases, it may be a result of a growing tumour, inflammation from a fracture in the lumbar spine, or an infection.

Spinal or foraminal stenosis can cause sciatica.
Sciatica – Nerve root compression

Sciatica pain due to piriformis syndrome.

Compression can also occur at the sciatic nerve as it passes through the piriformis muscle in the buttocks, which results in piriformis syndrome.

Do I need immediate medical attention?

Some medical conditions present with other symptoms on top of sciatica symptoms mentioned above and is in fact not a result of compression of the sciatic nerve. If you are also experiencing severe pain, difficulty with bowel or bladder control, and you are experiencing numbness in the inner thigh and groin area on top of the common symptom of back pain, you may have cauda equina syndrome and require immediate medical attention.

Unlike sciatica, cauda equina syndrome is a result of compression of the nerve bundle at the base of the spine, and may result in permanent nerve damage and loss of function if not treated quickly.

What is the sciatic nerve?

The sciatic nerve is the widest and longest nerve in the human body. Spinal nerves emerging from the lumbar spine and sacrum unite together to form the sciatic nerve which passes beneath the piriformis muscle and into the posterior thigh.

Sciatica is pain from the sciatic nerve. A group of nerves which travel from the spine to your foot.

Who is at risk of developing sciatica?

While anyone can develop sciatica, there are several factors that can increase these chances. Common risk factors associated with sciatica and back pain include increased age, reduced activity level, sedentary lifestyle, obesity, pregnancy, and occupation which requires prolonged sitting, exposure to vibrations, repetitive twisting, or heavy lifting.

How is sciatica diagnosed?

In order to diagnose sciatica, your primary care provider will require a complete medical history and perform a physical and neurological examination. Your medical history and the result of your physical examination will help narrow down possible diagnosis and ensure that you are provided with the appropriate treatment.

Imaging for Sciatica symptoms?

You may also be referred for imaging tests such as an MRI scan in order to gain a better understanding of what is causing sciatica like pain. Imaging tests will reveal presence of herniated disks or other space occupying lesions resulting in spinal stenosis or compression of the spinal cord and nerve roots.

Treatment for sciatica?

In keeping with best practice back pain care. Sciatica treated with conservative treatment is usually the first recommendation. Physical therapy and massage therapy may be used in combination with exercise recommendations in order to improve mobility and musculoskeletal function, as well as to improve strength of the core and back muscles. Other treatments including alternative therapies such as acupuncture may also be used to relieve pain and promote healing.

Your primary care provider may recommend taking over-the-counter anti-inflammatory medications or provide you with prescription medications such as muscle relaxants to help reduce pain while you seek other treatment options to address what is creating compression of your sciatic nerve, for instance a herniated disc. Steroid injections may also be offered to reduce inflammation and therefore reduce pain.

When Sciatica symptoms persist?

In the case where severe pain persists despite conservative treatment and a clear structural problem can be identifies, such as a herniated disk, surgical procedure may be performed.  

Diagnosis of slower back pain may involve imaging.

Do epidural steroid injections help with sciatica pain?

Steroid injections are administered to reduce inflammation which could help to decrease compression to the sciatic nerve and decrease pain. The effect of steroid injections may wear away after a few weeks however and you may start experiencing back pain again. Steroid injections often may be administered to decrease pain enough to allow conservative treatment or alternative therapies to take place.

Are there methods to prevent sciatica?

Maintaining proper posture when you are sitting can help reduce compression and compromise of the neuromusculoskeletal structures of your back and improve back pain in general. Having poor posture habitually while sitting may create reduction of space and mobility in the lumbosacral spine which may in turn develop into back pain and sciatica.

If you have chronic sciatica and are dealing with chronic pain, at home self care treatments may be beneficial to maintain mobility and flexibility of your spine. At home self care treatments aim to maintain low levels of pain and inflammation and include heat therapy, gentle stretching and exercise routine. Self care measures alone however may not be enough in the case of acute pain due to acute sciatica. It is important to consult a healthcare professional for proper diagnosis and treatment plan, so that it does not develop into chronic sciatica and long term repetitive back pain.

Having correct posture can help prevent sciatica.

When is surgery needed for sciatica?

In cases where permanent loss of function and muscle weakness due to neurological injury is a possibility, such as in the case of cauda equina syndrome, surgery will need to be performed. If you are experiencing unrelenting severe pain accompanied with progressive loss of neurological functions, surgery will be considered.

Use of surgery to treat sciatica depends on the underlying cause of nerve compression. In cases where sciatica is caused by an identifiable structural problem, such as a herniated disk, a surgical procedure, in this case a discectomy, may be done to remove the nerve compression. Physical therapy may be necessary following surgery to rehabilitate musculoskeletal function and movement.

Does physical therapy help with sciatica pain?

Physical therapy in combination with massage therapy and the prescription of an exercise program may be used to treat sciatica pain by improving mobility and musculoskeletal function, as well as improving strength of the core and back muscles. In certain cases, physical therapy may be enough to reduce compression of the sciatic nerve and resolve sciatica pain. You will also be provided with self care measures that you can do at home following treatment to maintain mobility, improvements in pain level and inflammation following treatment.

Physcial therapy can help sciatica.

Sciatica Recap

Sciatica is a deliberating condition that can affect all ages.

Sciatica present as pain from your lower back, which radiates down your leg along the length of the affected nerve. It may present with numbness, pins and needles or a burning sensation. In cases where the pain is not addressed, you may also experience leg weakness or foot drop.

It is important from a young age to be mindful of the long-term side effects of our actions. Degenerative disc or joint disease is a leading cause of sciatica pain in the patient we treat. This is often the result of deconditioning due to the underuse of the muscles which protect your spine.

It is important throughout your life to maintain your muscle strength and control of your spinal muscles. This decreases the risk of sciatica by ensuring your muscles are doing the work and not your joints or spinal discs.

Sciatica treatment recap.

If you are experiencing sciatica, the good news is that treatment options are available.

Treatment for sciatica will begin with physical therapy to alleviate your presenting pain, improve your postural control and retrain how you are moving to prevent further injury. If physical therapy does not alleviate all your symptoms, you may require surgery.

Surgery will take pressure off your sciatic nerve. However, remember it is important post-surgery to participate in an active rehabilitation plan to maintain the results and prevent a regress in symptoms.  

If you are looking for conservative treatment for sciatica in Sydney or need a rehabilitation plan.  Feel free to get in touch with us! We’re always here to help and would love to hear from you. 
A young female practitioner performing a hip stretch on a male patient.

Can you benefit from care?

Let us help you with tailor-made care designed for you

Check out some blogs about how care can help you

Chiropractic
Learn about how chiropractic can help you
Osteopath
Learn about how osteopath can help you
Functional Exercise
Exercise can be fun and easy. One exercise can change alot
Massage
There are both relaxing and therapeutic benefits to massage
Health Span
How looking after yourself along the way pays off
Five Dock Osteo Chiro
A bit about how we can help you

Do You Want To Feel Better?

drop us a line and keep in touch

Five Dock Osteopathic and Chiropractic male chiropractor wearing a light blue shirt performing a stretch on the neck of a young female patient. The doctors right hand is placed on the head of the patient and the left hand on the shoulder of the female patient